Acute stress and clinical reasoning: what changes


Table of contents
- What acute stress is in clinical practice
- What the studies show
- Threat or challenge: how the scene is read changes the body
- Signs that stress is weighing on you
- Quick techniques to use in the scene
- How to train reasoning for pressure
- Limits of the evidence
- How NEXO helps train this reasoning
- Frequently asked questions
- Take-home messages
- References
The emergency room is full. The monitor beeps, a family member asks loudly what is happening, and the resident has to decide in seconds whether the shortness of breath is from the heart or the lung. He knows the answer by heart when he studies at home. There, with his heart racing, the list of hypotheses shrinks to just one.
This narrowing has an explanation. Acute stress changes how the brain filters information, how the team talks and how the diagnosis closes. This text shows what simulation and practice studies found, which signs indicate that stress has started to weigh, and which techniques, simple and trainable, help keep clinical reasoning working under pressure.
Key points
- Acute stress impaired technical and non-technical skills in simulated and real surgical procedures (Tam, 2025).
- Noise and an insistent family member worsened teamwork in a simulated resuscitation (Krage, 2017).
- Seeing the scene as a challenge, not as a threat, was linked to better clinical performance (Betson, 2025).
- Time pressure and case framing changed the diagnostic reasoning of emergency physicians (Monick, 2025).
- A few minutes of slow breathing reduced a biological marker of stress (Dillard, 2023).
- Training with simulation and gradual exposure to stress helps the team think better in the real scene (Blanchard, 2024).
Summary
- What acute stress is in clinical practice
- What the studies show
- Threat or challenge: how you read the scene changes the body
- Signs that stress is weighing
- Quick techniques to use in the scene
- How to train reasoning for pressure
- Limits of the evidence
- How NEXO helps train this reasoning
- Frequently asked questions
- Take-home messages
What acute stress is in clinical practice
Acute stress is the body's and mind's quick response to a situation perceived as demanding or dangerous. The heart speeds up, breathing changes, attention narrows and the body prepares to act. This response lasts minutes or hours and passes when the situation ends.
It is different from chronic strain. Burnout and moral injury build up over months. Acute stress appears in a cardiac arrest, a difficult airway, a tense conversation with the family or a decision that has to come out in seconds.
A little activation helps. It keeps the professional alert, fast and focused. The problem starts when activation goes past the point and attention becomes so narrow that important information stops coming in. It is in this range that clinical reasoning starts to fail.
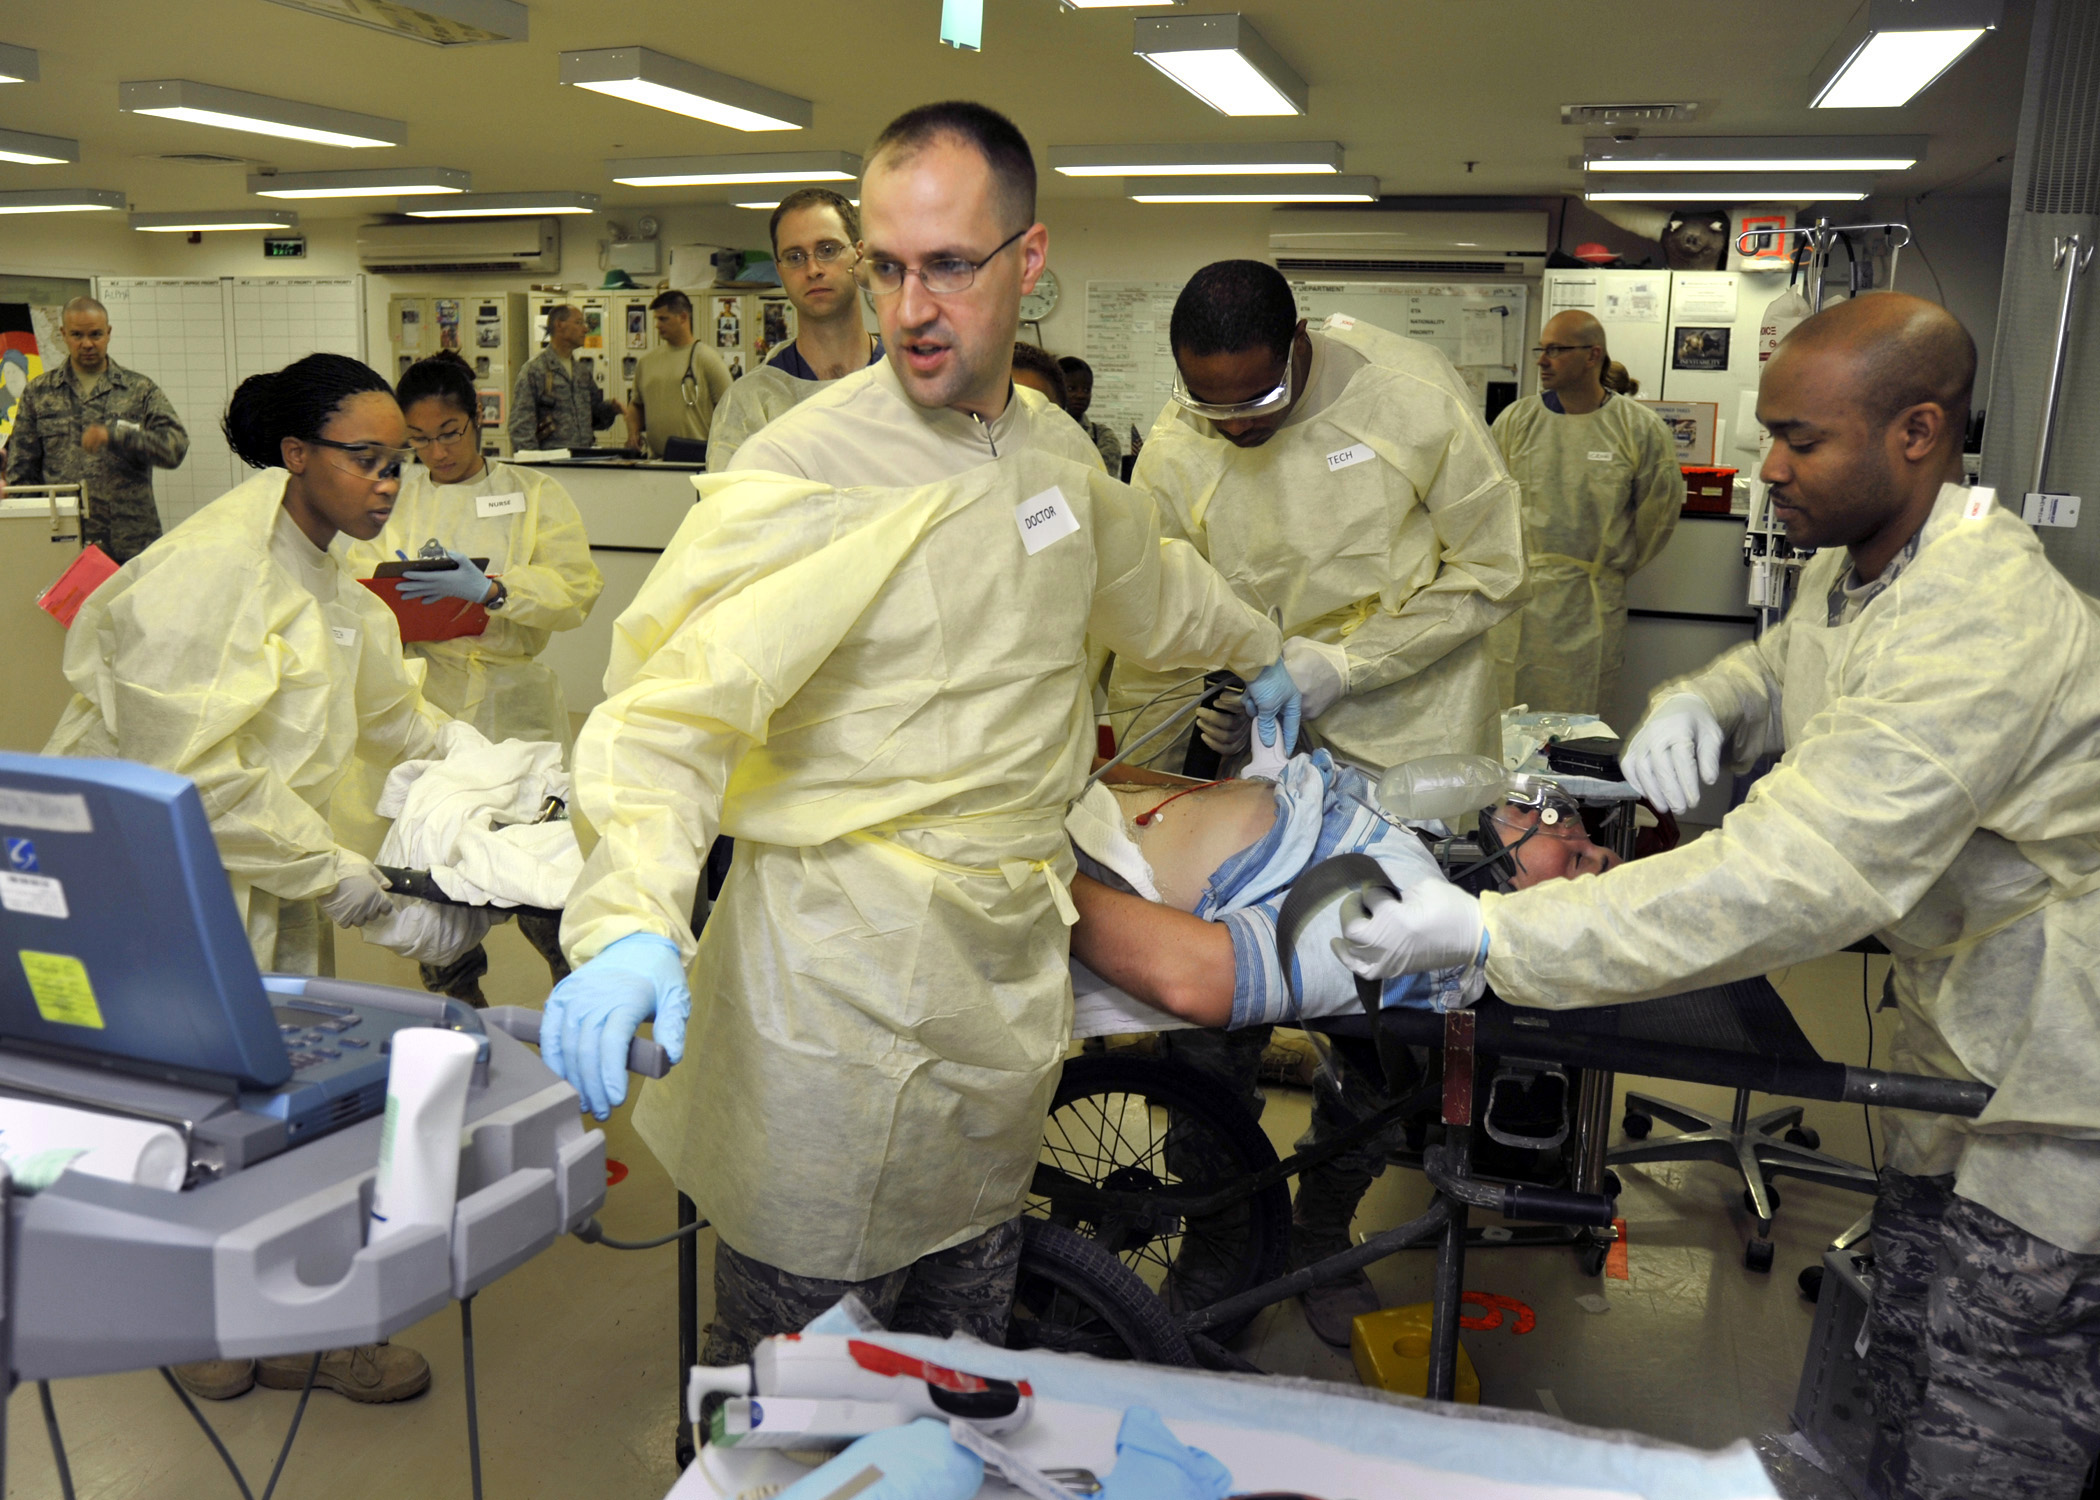
Think of a common scene in the emergency department. A patient arrives with intense shortness of breath, saturation drops, the monitor beeps and a family member asks loudly for explanations. The resident in charge feels the heart speed up and fixates on the oximeter. He orders oxygen, repeats the order twice and only then notices that no one measured the blood pressure or auscultated the chest calmly. The knowledge was there. What was missing was mental space to use it in the right order.
This scene shows why acute stress matters for clinical reasoning. It rarely appears as a lack of knowledge. It appears as a forgotten question, a hypothesis no one considered, an instruction that got lost in the noise.
The measurement of stress also varies. A systematic review of 61 articles on stress in surgical teaching environments found heart rate as the most used physiological measure, alongside short anxiety scales (Tjønnås, 2022). Measuring matters, because the subjective feeling does not always follow the body's response.
At the level of thought, the effect appears in attention and memory.
Under acute stress, the brain gives priority to what seems urgent. Attention concentrates on the strongest stimulus, such as the monitor alarm or visible bleeding, and the rest stays in the background. This helps act fast, but it also makes you miss details.
Working memory, which holds information while you think, has limited capacity. Stress takes up part of that space with worry and body signals. Less room is left to hold several hypotheses at the same time, compare data and remember what still needs checking.
That is why reasoning tends to become more automatic. The dual-process theory describes two modes of thinking: one fast and intuitive, the other slow and analytical. Under stress, the fast mode dominates, and the analytical mode, which corrects the errors of intuition, comes in less.
Students know this effect at exam time. Anxiety affects the reasoning of those who know the content and then freeze when they have to use it. In the clinical scene, the mechanism is similar, with one difference: the decision has an immediate consequence for the patient.
There is also an effect on the perception of time. Under stress, a few minutes feel like seconds, and the sense of urgency leads to skipping steps that, in calm conditions, would be automatic. That is why experienced teams often call out the time aloud and assign someone to watch the clock, freeing the leader to think.
What the studies show
Most of what is known comes from simulation. It allows the same scene to be created with and without stressors and performance to be compared, something impossible in real care.
In a crossover study, 30 anesthesiologists and residents conducted two simulated resuscitations, one of them with radio noise and a scripted family member who interrupted the team (Krage, 2017). With the stressors, non-technical performance dropped, with an adjusted mean difference of 3.9 points (Krage, 2017).
The most interesting finding was another one. With stressors, non-technical performance began to move together with technical performance, with a correlation of 0.67; without stressors, the correlation was only 0.15 (Krage, 2017). Leadership, communication and team organization mattered more precisely when the scene became difficult.
In practice, this means that training only the technical side is not enough. A team that knows the compression sequence but loses coordination when someone shouts at the door will make mistakes exactly at the moment the patient most needs it. Training non-technical skills, such as leadership, task distribution and clear communication, protects the technical side when the scene gets tense.
A systematic review on surgery found 19 eligible studies among 1445 identified (Tam, 2025). In simulated environments, acute stress consistently impaired technical and non-technical skills, such as teamwork and communication. Studies in real environments showed the same pattern, with more errors under stress (Tam, 2025).
Studies on diagnosis show a similar picture. The effect of stress on diagnosis depends on the context. A narrative review analyzed 25 studies, among 22,296 results, on how context affects physicians' clinical reasoning (Mason, 2020). The factors fell into three groups: patient, physician and environment.
Environmental factors included time pressure, an unfamiliar environment, uncertainty and high risk. Among physician factors, experience, prior exposure to similar diagnoses, wrong diagnostic suggestions and emotions appeared (Mason, 2020). Acute stress often brings several of these factors together in the same scene.
A study with 39 participants tested two of them in a controlled way (Monick, 2025). Participants analyzed cases of shortness of breath in versions that highlighted one hypothesis or another, with and without a time limit. The framing of the case and time pressure influenced diagnostic reasoning independently (Monick, 2025).
This connects with premature closure: under pressure, the first plausible hypothesis gains strength and the search ends early. Diagnostic uncertainty becomes more uncomfortable when the clock is running, and the discomfort pushes toward a quick answer.

Threat or challenge: how the scene is read changes the body
The same situation can be read in two ways. In the threat reading, the person feels that the demand exceeds their own resources. In the challenge reading, they feel they have what they need to face the scene.
A study with 26 paramedic students measured these readings before a high-pressure simulated practical assessment (Betson, 2025). Those who arrived with a challenge reading had more regulated cardiovascular and brain responses and higher clinical performance scores. Those who arrived with a threat reading had more physiological activation, increased cortisol and lower clinical competence (Betson, 2025).
Reading the scene can be trained. Remembering what has already been prepared, dividing the task into steps and naming the next concrete step help move from the feeling of threat to that of challenge.
Preparation before the shift also counts. Reviewing the protocols for the most feared situations, knowing where the materials are and agreeing with the team on who takes each role reduce the number of decisions that need to be made in the heat of the scene. Every decision made beforehand is one less decision competing for working memory later.
Emotional competence also matters. A scoping review on emotion and clinical reasoning concluded that the effect of emotional competence on reasoning was more evident under high acute stress, probably because of the greater cognitive load of these situations (Joly, 2026). Intense emotions can also distort judgment in other ways, as in affective bias.
Signs that stress is weighing on you
Recognizing stress in the moment is the first step to acting on it. Some signs appear in the body, others in the team's behavior.
- You notice you are looking at only one piece of data, such as the monitor, and have stopped seeing the patient.
- The list of hypotheses has shrunk to one, and new information seems to change nothing.
- You repeat an action that did not work instead of changing strategy.
- Instructions to the team become short, vague or contradictory.
- No one knows for sure who is leading or who does what.
- You feel short of breath, your hands tremble or your mind goes blank.
Any of these signs is a reason for a short pause. Ten seconds to breathe, summarize out loud and ask the team for ideas cost little and can change the course of the scene.
The signs also apply to those observing. A colleague who notices the leader fixed on a single piece of data can help with a simple sentence, such as "shall we summarize what we have?". Teams that agree on this kind of intervention beforehand make it easier to speak up without seeming to challenge the leadership.


Quick techniques to use in the scene
Some techniques fit in the middle of a call. They do not eliminate stress, but they give back part of the ability to think.
Slow breathing is the simplest. In a study with 79 participants undergoing high-tension virtual reality training, five minutes of slow breathing before and after the exercise reduced salivary alpha-amylase, a stress marker, 5 and 30 minutes later, compared with normal breathing (Dillard, 2023). The study was done outside health care, but the mechanism is the same.
In the scene, a short version can be used before entering the room or during a planned pause:
- Stop for a few seconds and exhale slowly.
- Say out loud what you already know about the case.
- Ask the team what might be missing.
- Name the next action and who will do it.
- Set a moment to reassess.
This sequence works as a diagnostic pause adapted to the urgency. Summarizing out loud organizes thinking, and asking the team recovers information that stress has hidden.
Closed-loop communication also helps. Whoever makes a request repeats it, whoever carries it out confirms out loud. This reduces the memory load and prevents an order from getting lost in the noise, exactly the kind of failure that stressors caused in simulated resuscitation (Krage, 2017).
How to train reasoning for pressure
Quick techniques work better when they have been trained beforehand. Training with controlled stress prepares body and mind for the real scene.
Stress inoculation exposes the professional to stressors gradually, with coping techniques taught beforehand. One study combined this approach with virtual reality for malignant hyperthermia management (Blanchard, 2024). The module induced stress, was well rated, and the results suggested that repeated exposure may desensitize participants to future stressors in a simulated setting (Blanchard, 2024).
A simulation program for medical trainees taught stress management techniques such as goal setting, visualization, self-talk, muscle relaxation, attention control and tactical breathing (Smith, 2021). Participants' confidence in using these techniques increased and was maintained three months later (Smith, 2021).
A pilot study tested device-guided mindfulness meditation practiced at home for four weeks by resuscitation teams (Kelm, 2018). Emotional balance improved, and participants reported a change in how they react to stress at work, including real resuscitations (Kelm, 2018).
The debriefing closes the loop. Talking after the scenario about what was felt, what was thought and what would be done differently turns the stress experienced into learning.
Preceptors play an important role in this training. When running a difficult scenario, the preceptor can think aloud, showing how they prioritize, when they pause and how they ask for help. This example teaches the resident that feeling stress is expected and that there are concrete ways to handle it without losing control of the case.
Students can also train outside formal simulation. Reviewing clinical cases under time pressure, explaining the reasoning aloud to a colleague and practicing slow breathing before practical exams are accessible ways to build familiarity with pressure.
The strategies have different goals and timing. The table summarizes what each one does and what the evidence shows.
| Strategy | When to use | What it does | Evidence |
|---|---|---|---|
| Slow breathing | Before or during pauses | Reduces physiological activation | Lower salivary marker (Dillard, 2023) |
| Challenge appraisal | Before the scenario | Changes the body's response and performance | Higher grades (Betson, 2025) |
| Pause and summarize aloud | During the scenario | Recovers hypotheses and organizes the team | Clinical practice |
| Stress inoculation | In training | Exposes to stressors gradually | Desensitization in simulation (Blanchard, 2024) |
| Stress management program | In training | Teaches coping techniques | Confidence maintained (Smith, 2021) |
| Mindfulness | Routine outside shifts | Improves emotional balance | Pilot study (Kelm, 2018) |
Choosing among these strategies depends on the moment and the professional. On the eve of a difficult shift, reviewing protocols and combining roles with the team carry more weight. At the start of the scenario, challenge appraisal and slow breathing help you enter with an organized mind. During the scenario, the short pause, the summary aloud and closed-loop communication sustain reasoning. Afterwards, debriefing and attention to one's own distress close the loop.
For those who coordinate training, the message is similar. Simulation programs can include realistic stressors such as noise, interruptions and anxious family members, as long as there is a safe debriefing afterwards. Exposure without a later conversation risks only frightening. Exposure with reflection teaches the trainee to recognize their own signals and to test strategies in a setting where mistakes cost the patient nothing.
It is also worth looking at the work environment. Unnecessary noise, alarms without priority, frequent interruptions and a lack of defined roles increase the load on those who make decisions. Simple adjustments to the organization of the emergency room, such as fixed places for materials and one person responsible for talking with the family, reduce stressors before the scenario even begins.
Rest remains irreplaceable. A well-trained but exhausted team loses part of the advantage that training gave, and schedules that respect breaks are part of prevention.

Limits of the evidence
Almost all the evidence comes from simulation. Simulation allows stressors to be controlled, but the real scene has consequences that no simulation fully reproduces. Transferring the results is a reasonable assumption, still little measured.
The studies are also small. Many have a few dozen participants, and stress measures vary widely between them (Tjønnås, 2022). Part of the evidence on techniques comes from outside health care, such as the slow breathing study (Dillard, 2023).
Acute stress also coexists with other factors. Poor sleep, hunger and long shifts increase vulnerability, and sleep deprivation during shifts deserves attention of its own. After a bad outcome, the distress of the second victim can turn the stress of the scene into something longer lasting.
Finally, the stress response varies between people and over the course of a career. Experience helps, because it turns new situations into familiar ones, but it can also create overconfidence. The techniques described here work as support, and each professional needs to find out which ones suit their way of working best.
How NEXO helps train this reasoning
In NEXO, the case of the day is fictional, with a real clinical presentation and up to six progressive clues, and you propose the diagnosis by looking for the code in ICD-10.
The limits on using the game are described on the NEXO economy page. If you research the teaching of clinical reasoning, the page for researchers explains how to get in touch. Professionals who write or review cases find information under curation and under creators, and institutions can learn about the proposal on the partnerships page. Training differential diagnosis with clues and looking for the right ICD-10 code complete this practice.
Frequently asked questions
Does acute stress always make clinical reasoning worse?
A little activation keeps the professional alert and quick. The harm appears when activation goes past the point and attention narrows too much. In surgery, acute stress impaired technical and non-technical skills (Tam, 2025).
Why does teamwork get worse under stress?
Noise and interruptions compete for the leader's attention. In a simulated resuscitation, the stressors reduced non-technical performance, and that performance came to weigh more on the technical outcome (Krage, 2017).
Does time pressure change the diagnosis?
Yes. In a study with cases of shortness of breath, time pressure and how the case was framed influenced reasoning independently (Monick, 2025).
Does breathing slowly really help?
A few minutes of slow breathing reduced a biological marker of stress in a high-tension training session (Dillard, 2023). In the scene, a short pause with slow exhalation can be combined with a summary out loud.
Can the stress response be trained?
Yes. Programs with simulation increased confidence in managing stress for at least three months (Smith, 2021), and gradual exposure in virtual reality suggested desensitization (Blanchard, 2024).
What should be done after a very stressful scene?
Hold a debriefing with the team, talk about what was felt and what was learned, and seek support if the distress persists. The stress of a difficult scene can become prolonged distress when no one talks about it.
Take-home messages
- Acute stress narrows attention, occupies working memory and favors automatic thinking.
- Noise, interruptions and time pressure make teamwork and diagnostic reasoning worse.
- Seeing the scene as a challenge, with resources and clear steps, changes the body's response and performance.
- Slow breathing, a summary out loud and closed-loop communication fit in the middle of care.
- Simulation with controlled stress and debriefing prepare the team before the real scene.
- The evidence still comes mostly from simulation, and transfer to practice needs more studies.
Want to train clinical reasoning with time to think and learn from each clue? Play the case of the day on NEXO.
References
- Betson J, Fein EC, Long D, et al. Relationships between cognitive appraisals of threat and challenge, psychophysiological responses, and clinical performance during high-stress simulated OSCEs. BMC Med Educ. 2025. PMID 41331936. DOI 10.1186/s12909-025-08365-3.
- Blanchard EE, Trost Z, Brown MR, et al. Combining stress inoculation with virtual reality simulation training of malignant hyperthermia. Adv Simul (Lond). 2024. PMID 39152517. DOI 10.1186/s41077-024-00308-0.
- Dillard CC, Martaindale H, Hunter SD, et al. Slow Breathing Reduces Biomarkers of Stress in Response to a Virtual Reality Active Shooter Training Drill. Healthcare (Basel). 2023. PMID 37628548. DOI 10.3390/healthcare11162351.
- Joly L, Nunes de Sousa A, Bardiau M, et al. Impact of emotional competence on clinical reasoning: a scoping review. BMJ Open. 2026. PMID 42259553. DOI 10.1136/bmjopen-2025-113483.
- Kelm DJ, Ridgeway JL, Gas BL, et al. Mindfulness Meditation and Interprofessional Cardiopulmonary Resuscitation: A Mixed-Methods Pilot Study. Teach Learn Med. 2018. PMID 29775080. DOI 10.1080/10401334.2018.1462186.
- Krage R, Zwaan L, Tjon Soei Len L, et al. Relationship between non-technical skills and technical performance during cardiopulmonary resuscitation: does stress have an influence? Emerg Med J. 2017. PMID 28844039. DOI 10.1136/emermed-2016-205754.
- Mason A, Locke R, Lusznat RM, et al. How Do Contexts Affect Physicians' Clinical Reasoning? A Narrative Review. MedEdPublish (2016). 2020. PMID 38058867. DOI 10.15694/mep.2020.000032.1.
- Monick AJ, Zhang XC. Cognitive Frame and Time Pressure as Moderators Of Clinical Reasoning: A Case Control Study. West J Emerg Med. 2025. PMID 40795018. DOI 10.5811/westjem.24851.
- Smith S, Kassam A, Griggs L, et al. Teaching mindfulness-based stress management techniques to medical learners through simulation. Can Med Educ J. 2021. PMID 33680238. DOI 10.36834/cmej.69821.
- Tam A, Bateman S, Buckingham G, et al. The effects of stress on surgical performance: a systematic review. Surg Endosc. 2025. PMID 39627555. DOI 10.1007/s00464-024-11389-3.
- Tjønnås MS, Guzmán-García C, Sánchez-González P, et al. Stress in surgical educational environments: a systematic review. BMC Med Educ. 2022. PMID 36380334. DOI 10.1186/s12909-022-03841-6.