Tobacco: less exposure is not always less risk

Table of contents
- Exposure and risk: two different questions
- The curve that is not straight: why smoking little still weighs
- Reducing the number of cigarettes: what the cohorts show
- Compensation: how the smoker adjusts the puff
- The lesson of light cigarettes
- Biomarkers of exposure and of harm: what each one proves
- From biomarker to disease: surrogate outcomes and their limits
- How to use this reasoning in the consultation
- Frequently asked questions
- Final checklist
- References
At the follow-up visit, he arrives pleased. He used to smoke a pack a day and now smokes five cigarettes. He switched to a "lighter" version and says the previous doctor praised the change. He asks whether, with that, he can already be at ease about his heart. The honest answer is uncomfortable: exposure fell, but the risk of disease did not fall in the same proportion, and in some cases it barely fell.
This text deals with a common confusion in the clinic and when reading articles: treating exposure and risk as if they were the same thing. Let us see why the curve between cigarettes and disease is not straight, what happens when someone reduces the number of cigarettes, how the smoker compensates without noticing, what light cigarettes taught us and how to read biomarkers without taking from them more than they prove.
Key points
- Less measured exposure does not guarantee less disease; they are different questions, which call for different evidence.
- For the heart, smoking little carries about half the risk of smoking a lot, not a twentieth.
- Reducing the number of cigarettes lowers the risk of lung cancer far less than quitting does.
- The smoker compensates: inhales deeper, smokes more often, covers the filter holes.
- Light cigarettes reduced machine numbers, not real exposure or disease.
- An exposure biomarker and a damage biomarker are different steps, and neither of them is the disease.
Summary
- Exposure and risk: two different questions
- The curve that is not straight: why smoking little still weighs
- Reducing the number of cigarettes: what the cohorts show
- Compensation: how the smoker adjusts the puff
- The lesson of light cigarettes
- Exposure and damage biomarkers: what each one proves
- From biomarker to disease: surrogate outcomes and their limits
- How to use this reasoning in the consultation
- Frequently asked questions
- Final checklist
Exposure and risk: two different questions
When people talk about "tobacco harm reduction", two questions usually appear mixed together. The first is whether a product or behavior decreases the amount of toxic substances that reaches the body. The second is whether that decrease is reflected in fewer heart attacks, fewer strokes, less cancer and fewer deaths. The first question is answered in weeks, with measurements in blood, urine or exhaled air. The second requires years or decades of follow-up.
A committee of the Institute of Medicine organized exactly this distinction when evaluating products that promised to preserve the pleasure of tobacco with fewer toxic effects (Institute of Medicine, 2001). The report separated three questions: whether the product decreases exposure to harmful substances, whether lower exposure is associated with less harm to health and whether there are surrogate indicators of harm that can be measured quickly enough to guide decisions (Institute of Medicine, 2001). The order matters. Answering yes to the first does not answer the second.
For the clinician, this separation has a direct consequence. When someone says they "now smoke less", that is a statement about exposure. What matters for prognosis is risk, and the relationship between the two depends on the shape of the dose-response curve, on the person's actual behavior and on the outcome being discussed. It is the same care taken when interpreting any clinical data: the value only gains meaning when you know what it represents and for which outcome, as discussed in the text on pretest probability.
Three ideas organize the rest of the text:
- The curve between amount smoked and disease is not linear for all outcomes.
- The amount reported is not the amount inhaled.
- A biomarker that falls is not, by itself, a disease that stops happening.
The curve that is not straight: why smoking little still weighs
If risk were proportional to the number of cigarettes, someone who goes from 20 to one cigarette a day would have a twentieth of the excess risk. For lung cancer, the relationship between risk and number of cigarettes is roughly linear, but for cardiovascular disease the curve rises steeply even at low consumption and then flattens, and the same non-linear pattern appears in stroke (Hackshaw and colleagues, 2018).
A meta-analysis pooled 141 cohort studies published in 55 articles to measure the risk of coronary heart disease and stroke in light smokers (Hackshaw and colleagues, 2018). Among men, the relative risk of coronary heart disease was 1.48 for one cigarette per day and 2.04 for 20 cigarettes per day, considering all studies (Hackshaw and colleagues, 2018). In studies adjusted for multiple confounders, the values were 1.74 and 2.27 (Hackshaw and colleagues, 2018). Among women, the relative risks were 1.57 and 2.84, or 2.19 and 3.95 with multiple adjustment (Hackshaw and colleagues, 2018).
For stroke, the pattern repeated. In men, the relative risks were 1.25 and 1.64 for one and 20 cigarettes per day; in women, 1.31 and 2.16 (Hackshaw and colleagues, 2018). The authors concluded that smoking about one cigarette per day carries a risk of coronary heart disease and stroke much higher than expected, around half the risk of smoking 20 per day, and that there is no safe level of smoking for cardiovascular disease (Hackshaw and colleagues, 2018).
In the full text, the authors explain that the expectation of proportionality, in which one cigarette per day would carry a twentieth of the risk of 20, seems to hold for lung cancer but not for coronary heart disease and stroke (Hackshaw and colleagues, 2018). They also discuss the plausible mechanisms: smoke components cause endothelial injury, cell dysfunction, atherosclerosis, acute thrombosis and a reduced capacity of the blood to carry oxygen, and several of these effects appear even at low exposures (Hackshaw and colleagues, 2018).
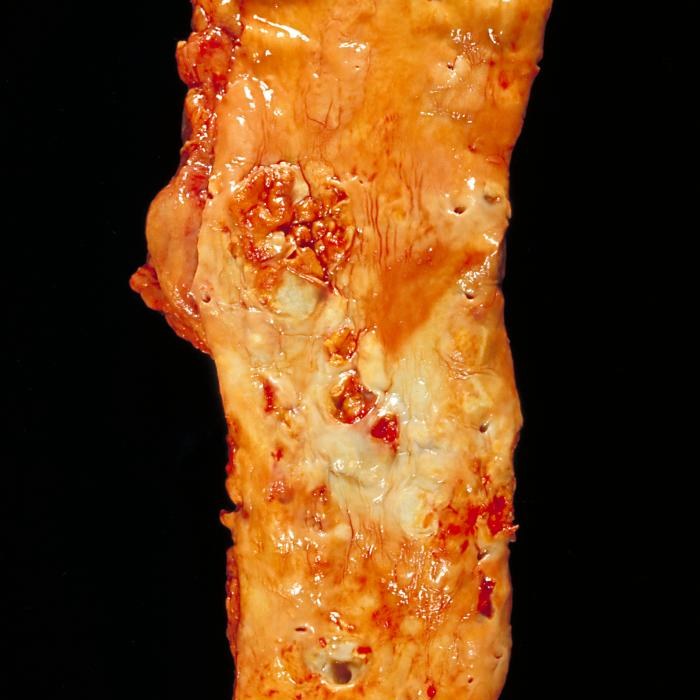

Light smoking over an entire lifetime also takes its toll. In a cohort of 290215 adults aged 59 to 82, those who consistently smoked less than one cigarette per day had a higher risk of death from any cause than those who never smoked, with a hazard ratio of 1.64 (Inoue-Choi and colleagues, 2017). For those who consistently smoked one to ten cigarettes per day, the hazard ratio was 1.87 (Inoue-Choi and colleagues, 2017). The association was especially strong with lung cancer, with hazard ratios of 9.12 and 11.61 in the two groups (Inoue-Choi and colleagues, 2017).
The same study brings a fact that often goes unnoticed: most people who smoked little at the time of the questionnaire had smoked considerably more at earlier stages of life (Inoue-Choi and colleagues, 2017). Someone who says "I smoke little" in the office may be describing the present, not the cumulative exposure. Asking about the history over the decades changes the estimate.
Reducing the number of cigarettes: what the cohorts show
If light smoking still weighs, what happens to those who smoked heavily and reduce? The question is reasonable, because many people who cannot or do not want to quit try to cut down the amount.
A population cohort followed 19714 adults who had two examinations five to ten years apart, with follow-up of up to 31 years for lung cancer (Godtfredsen and colleagues, 2005). Participants were divided according to their habit between the two examinations: heavy smokers who continued, reducers who cut at least half without quitting, light smokers who continued, those who quit, stable ex-smokers and those who never smoked (Godtfredsen and colleagues, 2005). During follow-up, 864 participants developed lung cancer (Godtfredsen and colleagues, 2005).
Compared with heavy smokers who continued, reducers had an adjusted hazard ratio of 0.73 for lung cancer (Godtfredsen and colleagues, 2005). Stable ex-smokers had 0.17 and those who never smoked, 0.09 (Godtfredsen and colleagues, 2005). The authors concluded that halving significantly reduces the risk of lung cancer among heavy smokers (Godtfredsen and colleagues, 2005). The clinical reading, however, must look at both sides: the benefit of reducing exists, but it falls far short of the benefit of quitting.
For the heart, the situation is even less encouraging, given the shape of the curve we saw above. The authors of the meta-analysis of cohorts sum up the recommendation directly: smokers should aim to quit rather than cut down, if they want to significantly lower the risk of coronary disease and stroke (Hackshaw and colleagues, 2018). In the full text, they discuss three large studies that specifically examined the effect of reduction on cardiovascular disease and note that few heavy smokers manage to reduce sustainably without quitting (Hackshaw and colleagues, 2018).
There is also a methodological problem. In cohorts, reduction is self-reported, and the number of cigarettes does not say how much of each cigarette the person inhales. This is where compensation comes in. That does not make reduction useless. It can be a legitimate intermediate step, and the reasoning of harm reduction helps negotiate goals without moralism. The point is not to confuse the intermediate step with the destination, and to keep the conversation about quitting open, as the text on smoking cessation at every visit proposes.
Compensation: how the smoker adjusts the puff
Nicotine is what sustains the dependence, and the body of a smoker tends to seek the amount it is used to. When a cigarette delivers less nicotine per puff, or when the person smokes fewer cigarettes, they adjust their behavior, usually without noticing: they inhale more deeply, hold the smoke longer, take more puffs per cigarette, smoke closer to the filter, or cover the small ventilation holes with fingers and lips.
This adjustment has been measured directly. In a three-week crossover study, smokers used their usual cigarette in the first and third weeks and, in the second, a light cigarette with a machine-measured nicotine yield of about half the usual (Benowitz and colleagues, 2005). By cotinine and carboxyhemoglobin, the average compensation was 78 and 83 per 100 parts of the expected reduction, respectively (Benowitz and colleagues, 2005). Urinary excretion of a tobacco-specific nitrosamine metabolite and of several polycyclic aromatic hydrocarbon metabolites was similar across the three weeks (Benowitz and colleagues, 2005).
The same study showed how compensation happens: participants smoked each cigarette more intensely and also smoked more cigarettes per day (Benowitz and colleagues, 2005). The authors' conclusion was that the short-term switch did not significantly reduce exposure to carcinogens and that switching to light cigarettes is unlikely to reduce the risks of smoking (Benowitz and colleagues, 2005).
For the visit, compensation has three practical implications:
- The reported number of cigarettes underestimates exposure when the person has reduced or switched products.
- The feeling of "smoking less" can be real in number of cigarettes and false in exposure.
- Nicotine withdrawal explains part of the difficulty of reducing: the body asks for the usual amount.
This does not mean doubting the patient. It means understanding that smoking behavior is regulated by mechanisms the person neither controls nor fully perceives, and that an honest report may not reflect what reaches the lungs.
The lesson of light cigarettes
Cigarettes sold as light or low-yield were, for decades, the main promise of "smoking with less risk". The argument seemed technical: standardized smoking machines measured less tar and less nicotine per cigarette. The problem is that machines do not compensate. People do.
A study of 150 smokers compared carcinogen biomarkers between those who usually used light cigarettes and those who used regular cigarettes (Bernert and colleagues, 2005). The authors measured cotinine, a urinary metabolite of a tobacco-specific nitrosamine, and hemoglobin adducts of a carcinogenic aromatic amine (Bernert and colleagues, 2005). There was no significant difference in these biomarkers between the two groups: concentrations in light smokers were essentially the same as in regular cigarette smokers (Bernert and colleagues, 2005).
The story did not end with exposure. The Surgeon General's 50-year report concluded that the evidence is sufficient to state that the risk of lung adenocarcinoma associated with cigarettes has increased since the 1960s and that this increase results from changes in the design and composition of cigarettes since the 1950s (US Department of Health and Human Services, 2014). The same report considered the evidence insufficient to point to which changes were responsible, but suggestive that ventilated filters and higher levels of tobacco-specific nitrosamines played a role (US Department of Health and Human Services, 2014).
The large cohorts tell the same story from another angle. Comparing three periods, the relative risk of death from lung cancer in women who smoke, compared with those who never smoked, was 2.73 in the 1960s cohorts, 12.65 in the 1980s cohorts and 25.66 in contemporary ones (Thun and colleagues, 2013). In men, the corresponding values were 12.22, 23.81 and 24.97 (Thun and colleagues, 2013). The authors concluded that the risk of death associated with cigarettes continued to rise among women and that, among men, it stabilized at the high levels of the 1980s (Thun and colleagues, 2013). These increases happened precisely in the period when cigarettes with lower machine-measured yields became widespread.
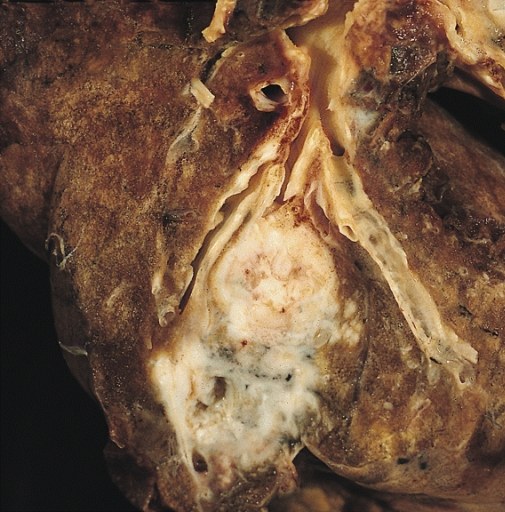

The lesson for clinical reasoning goes beyond the product. A number measured under standardized laboratory conditions was taken as if it were the real exposure and then as if it were the real risk. Two leaps of inference without verification. The same kind of leap appears whenever an intermediate result is sold as an outcome, and recognizing this pattern is a skill of critical reading.
Biomarkers of exposure and of harm: what each one proves
Biomarkers are indispensable for studying tobacco. They allow measuring in weeks what the disease would take decades to show. But each type of biomarker answers a different question, and confusing them is the source of many hasty conclusions.
Biomarkers of exposure show that a substance entered the body: cotinine for nicotine, exhaled carbon monoxide and carboxyhemoglobin for combustion products, urinary metabolites of nitrosamines and of hydrocarbons for carcinogens. Biomarkers of potential harm show a biological change that may lie on the path to disease: inflammation, oxidative stress, endothelial function, lung function. Disease is the clinical outcome itself.
A population study with 5105 adults measured 50 biomarkers from five classes of tobacco constituents in the urine of exclusive e-cigarette users, exclusive smokers, dual users and people who never used tobacco (Goniewicz and colleagues, 2018). Exclusive e-cigarette users had significantly lower concentrations of most biomarkers of exposure compared with exclusive smokers, but concentrations were comparable for metals and for three volatile organic compounds (Goniewicz and colleagues, 2018). Exposure was higher among dual users, and the frequency of cigarette use among them correlated positively with exposure to nicotine and to toxic substances (Goniewicz and colleagues, 2018). In the limitations section, the authors note that metals have a long half-life and may reflect previous exposures (Goniewicz and colleagues, 2018). It is worth flagging the conflict of interest: in the article's declaration, a coauthor reports frequent, unpaid contacts with an e-cigarette company between 2015 and 2020, and the first author reports consulting and funding from pharmaceutical companies (Goniewicz and colleagues, 2018).


The table below organizes the steps of evidence and what each one allows you to conclude.
| Level of evidence | What is measured | What can be concluded | What cannot yet be concluded |
|---|---|---|---|
| Laboratory emission | Substances in the smoke or aerosol, generated by the device | The product emits less of certain substances under the test conditions | How much the person inhales in real use |
| Biomarker of exposure | Cotinine, carbon monoxide, carcinogen metabolites | How much of the substance entered the body in the measured period | Whether there will be less biological change or less disease |
| Biomarker of potential harm | Inflammation, oxidative stress, endothelial or pulmonary function | Whether a change in the disease pathway has occurred | Whether clinical disease will be less frequent in the long term |
| Disease in a cohort | Heart attack, stroke, cancer, COPD, death | Association between the pattern of use and the outcome | Causality without considering confounding and selection bias |
A secondary systematic review of intervention studies shows the limits of the intermediate step well. It included 1299 adult smokers in nine studies and analyzed carbon monoxide and 26 other biomarkers (Hartmann-Boyce and colleagues, 2023). Comparing those who switched to e-cigarettes only with those who kept smoking, 12 of 13 biomarkers were significantly lower in the first group (Hartmann-Boyce and colleagues, 2023). Only one study compared dual use with exclusive cigarette smoking, and only one study provided data from those who quit everything (Hartmann-Boyce and colleagues, 2023). The authors themselves note that the data come from short-term confinement studies, poorly generalizable to real use, or from non-randomized groups, subject to confounding (Hartmann-Boyce and colleagues, 2023). Here too there are conflicts to flag: one author declares consulting and research funding from a pharmaceutical company, another declares consulting for a nicotine replacement manufacturer, and the characteristics table shows that two of the nine included studies had funding from the tobacco or e-cigarette industry (Hartmann-Boyce and colleagues, 2023).
From biomarker to disease: surrogate outcomes and their limits
In medicine, a surrogate outcome only counts as a shortcut when it has been shown that changing the marker changes the disease. This has happened in some cases, and failed spectacularly in others. With tobacco, the temptation to skip steps is great, because waiting decades for disease data is costly and slow.
The National Academies committee that reviewed the evidence on e-cigarettes shows how to make the distinction rigorously. It concluded that there is conclusive evidence that completely replacing cigarettes with e-cigarettes reduces exposure to numerous toxic substances and carcinogens present in cigarettes (National Academies of Sciences, Engineering, and Medicine, 2018). In the same report, however, it stated that no evidence was available on the effects of prolonged use on disease, and classified as "conclusive" only evidence with many favorable findings from good-quality controlled studies and no credible contrary findings (National Academies of Sciences, Engineering, and Medicine, 2018). Lower exposure with strong evidence, disease with absent evidence. Two true statements that do not contradict each other.
There are three main reasons why the step between biomarker and disease is not automatic:
- Different curves for different outcomes. A marker can fall in proportion to exposure, while cardiovascular risk, as we have seen, falls much less.
- Substances not measured. No panel covers everything, and disease may depend precisely on what was left out.
- Latency time. Lung cancer develops over decades, and markers measured in weeks do not capture this process.
The reverse path also misleads. When an observational study shows less disease in a group, the temptation is to attribute the result to the product. But those who switch products, reduce or quit tend to differ in many other things, and the reasoning must consider confounding and selection bias, topics covered in the text on study designs and their weaknesses. Interpreting a result in light of who is already known to have become ill is another trap, discussed in the text on retrospective bias.
How to use this reasoning in the consultation
What to do with all this in front of the patient from the opening scene? First, acknowledge the effort. He reduced, and that took work. Then, explain without lecturing why the reduction does not put the heart at ease, and keep the conversation about quitting open.
The benefit of stopping is large and depends on age. In a cohort of 34439 physicians followed for 50 years, men who smoked cigarettes continuously died on average about ten years earlier than those who never smoked (Doll and colleagues, 2004). Stopping at 60, 50, 40 or 30 years of age added, respectively, about 3, 6, 9 or 10 years of life expectancy (Doll and colleagues, 2004). In contemporary cohorts, stopping at any age sharply reduced death rates (Thun and colleagues, 2013). And even among those who always smoked little, the risk was progressively lower the earlier the person stopped (Inoue-Choi and colleagues, 2017).
Some questions help bring exposure and risk reasoning into the consultation:
- How much do you smoke today, and how much did you smoke in previous decades?
- Since you cut down, has the way you smoke changed? Do you inhale deeper, smoke to the end, feel more craving?
- What product do you use, and what have you heard about it?
- What would it mean for you to stop completely, and what gets in the way?
The first question corrects the idea that the present sums up the exposure. The second makes compensation visible. The third opens space to discuss product promises without confrontation. The fourth takes the conversation to the point that most changes the prognosis. To structure this short approach and choose the treatment, the guide in the text on treatment options for cessation is worth following.
There is also a point of diagnostic vigilance. Cumulative exposure guides the probability of disease in findings such as an incidental pulmonary nodule, and underestimating the smoking burden because of a report of "smoking little" distorts the estimate, as the text on probability before the rule shows. The same holds for screening for other substances: the patient's sentence is a datum, not the measurement, as the text on screening and pretest probability discusses.
Finally, it is worth watching your own reasoning. "Smokes little, so the risk is small" is a tempting mental shortcut, of the kind described in the text on when the heuristic helps and when it gets in the way. It works for lung cancer in a rough way and fails for the heart. Knowing where the shortcut breaks is part of clinical work.
Frequently asked questions
Does smoking few cigarettes a day protect the heart?
No. In a meta-analysis of 141 cohorts, smoking about one cigarette a day carried around half the risk of coronary disease and stroke of smoking 20 a day (Hackshaw and colleagues, 2018).
Does halving the number of cigarettes cut the risk in half?
Not necessarily. In a cohort, those who reduced by at least half had a hazard ratio of 0.73 for lung cancer compared with those who kept smoking heavily, far from the risk of those who stopped for good (Godtfredsen and colleagues, 2005).
What is compensation when smoking?
It is the unconscious adjustment of the way of smoking to maintain the usual nicotine: inhaling deeper, taking more puffs or smoking more cigarettes. In a crossover study, switching to a light cigarette was almost entirely compensated for (Benowitz and colleagues, 2005).
Why did light cigarettes not reduce disease?
Because they reduced numbers measured by machine, not the real exposure. Light smokers had biomarkers of carcinogens essentially equal to those of people smoking regular cigarettes (Bernert and colleagues, 2005).
Does a lower biomarker mean less disease?
Not automatically. There is strong evidence of lower exposure in some scenarios, but evidence is absent on long-term disease, as the National Academies review shows (National Academies of Sciences, Engineering, and Medicine, 2018).
Does this text guide treatment?
No. It is a text about reasoning and reading evidence. Treatment decisions depend on individual assessment and current guidelines, and the topic of cessation is covered in detail in another blog text.
Final checklist
- Separate the two questions: did exposure decrease? did disease decrease?
- Remember that, for the heart, smoking little still carries about half the risk of smoking a lot.
- Ask about the history of consumption over the decades, not only about the present.
- Ask whether the way of smoking changed after cutting down or switching products.
- Treat reduction as a possible step, not as the destination, and keep the conversation about stopping open.
- When reading a study, identify the step: emission, exposure biomarker, harm biomarker or disease.
- Look for the conflict of interest statement and the funding of the included studies.
- Do not accept a laboratory number as if it were the patient's real risk.
References
- Benowitz NL, Jacob P 3rd, Bernert JT, et al. Carcinogen exposure during short-term switching from regular to "light" cigarettes. Cancer Epidemiol Biomarkers Prev. 2005. PMID 15941944. DOI 10.1158/1055-9965.EPI-04-0667.
- Bernert JT, Jain RB, Pirkle JL, et al. Urinary tobacco-specific nitrosamines and 4-aminobiphenyl hemoglobin adducts measured in smokers of either regular or light cigarettes. Nicotine Tob Res. 2005. PMID 16191744. DOI 10.1080/14622200500259762.
- Doll R, Peto R, Boreham J, Sutherland I. Mortality in relation to smoking: 50 years' observations on male British doctors. BMJ. 2004. PMID 15213107. DOI 10.1136/bmj.38142.554479.AE.
- Godtfredsen NS, Prescott E, Osler M. Effect of smoking reduction on lung cancer risk. JAMA. 2005. PMID 16189363. DOI 10.1001/jama.294.12.1505.
- Goniewicz ML, Smith DM, Edwards KC, et al. Comparison of nicotine and toxicant exposure in users of electronic cigarettes and combustible cigarettes. JAMA Netw Open. 2018. PMID 30646298. DOI 10.1001/jamanetworkopen.2018.5937.
- Hackshaw A, Morris JK, Boniface S, Tang JL, Milenković D. Low cigarette consumption and risk of coronary heart disease and stroke: meta-analysis of 141 cohort studies in 55 study reports. BMJ. 2018. PMID 29367388. DOI 10.1136/bmj.j5855.
- Hartmann-Boyce J, Butler AR, Theodoulou A, et al. Biomarkers of potential harm in people switching from smoking tobacco to exclusive e-cigarette use, dual use or abstinence: secondary analysis of Cochrane systematic review of trials of e-cigarettes for smoking cessation. Addiction. 2023. PMID 36208090. DOI 10.1111/add.16063.
- Inoue-Choi M, Liao LM, Reyes-Guzman C, et al. Association of long-term, low-intensity smoking with all-cause and cause-specific mortality in the National Institutes of Health-AARP Diet and Health Study. JAMA Intern Med. 2017. PMID 27918784. DOI 10.1001/jamainternmed.2016.7511.
- Institute of Medicine; Stratton K, Shetty P, Wallace R, Bondurant S, editors. Clearing the Smoke: Assessing the Science Base for Tobacco Harm Reduction. National Academies Press. 2001. PMID 25057541. DOI 10.17226/10029.
- National Academies of Sciences, Engineering, and Medicine. Public Health Consequences of E-Cigarettes. National Academies Press. 2018. PMID 29894118. DOI 10.17226/24952.
- Thun MJ, Carter BD, Feskanich D, et al. 50-year trends in smoking-related mortality in the United States. N Engl J Med. 2013. PMID 23343064. DOI 10.1056/NEJMsa1211127.
- US Department of Health and Human Services. The Health Consequences of Smoking: 50 Years of Progress. A Report of the Surgeon General. 2014. PMID 24455788.