Thunderstorm asthma: pollen, weather and outbreaks
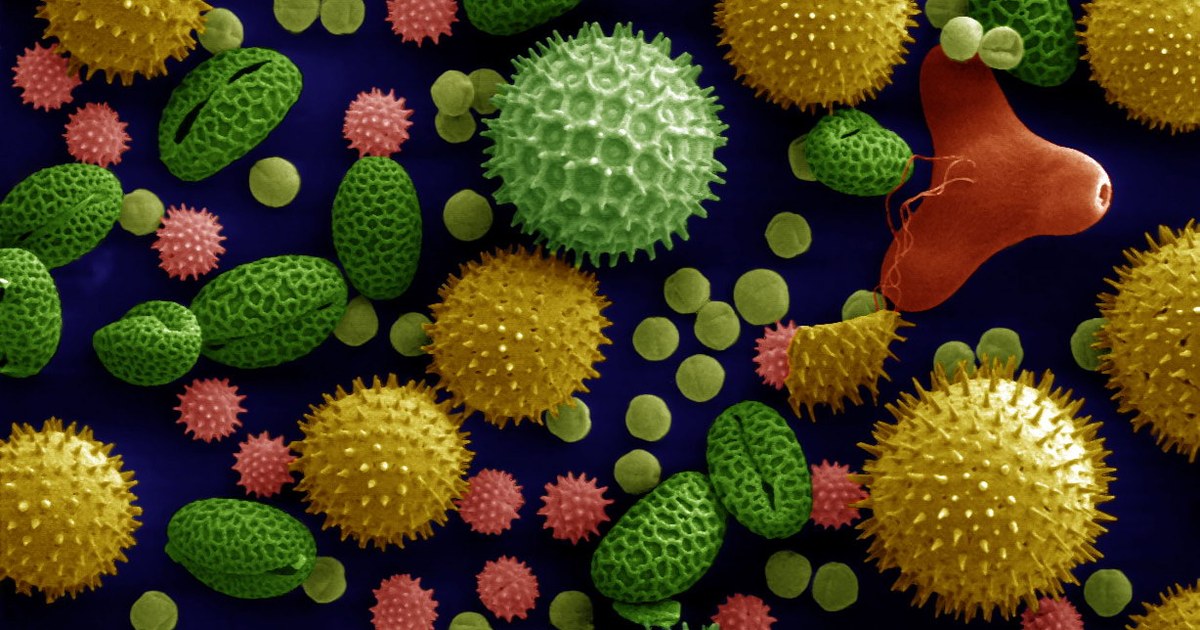
Table of contents
- Why thunderstorm asthma is a reasoning setting
- What happens in the air during the storm
- Outbreaks described in several places
- Who is most at risk
- Markers that help estimate risk
- After the outbreak: the asthma that stays
- Prevention, alert and action plan
- The biases that leave the weather out
- How NEXO helps train this reasoning
- Frequently asked questions
- Final checklist
- References
At the end of a hot spring afternoon, a storm passes through the city with strong wind and a sharp drop in temperature. Two hours later, the emergency department starts receiving people with shortness of breath and wheezing. One of them is a woman in her early thirties who has never been diagnosed with asthma. She says she gets rhinitis every year at this time and that she was walking home from work when the wind started. The scene is fictional and was written for teaching. This text uses that picture as a setting for clinical reasoning: how a storm can trigger mass asthma attacks, who is most at risk, which questions help recognize the pattern and what to do so that the next storm finds people better prepared.
NEXO is a daily medical diagnosis game: one clinical case a day, up to six progressive clues, and ICD-10 proximity feedback across five levels.
This text is not a guide to asthma treatment. Management of the attack and the control plan follow their own guidelines, and a service's response to an outbreak depends on local organization. The interest here is the reasoning: how weather and environment enter the story, and why a clue about yesterday can explain today's picture. If you play the case of the day on NEXO, you will recognize the move: a clue about the environment can change the course of the guess.
Key points
- Thunderstorm asthma is the appearance of acute asthma attacks soon after a storm, in pollen season.
- The combination of seasonal allergic rhinitis, sensitization to grass pollen and outdoor exposure during the storm forms the most described risk trio.
- Many affected people have never been diagnosed with asthma.
- Existing, poorly controlled asthma weighs in favor of more severe attacks.
- An outbreak can overwhelm emergency care within a few hours, and preparation begins before pollen season.
Why thunderstorm asthma is a reasoning setting
Harun and colleagues define thunderstorm-triggered asthma as the occurrence of acute asthma attacks soon after a storm, with epidemics described in various parts of the world during pollen season (Harun and colleagues, 2019). The authors note that these outbreaks can quickly overwhelm a health service, with potentially catastrophic outcomes for patients.
For the clinician, the topic is useful because it forces a look outside the patient. An isolated asthma attack usually leads to questions about adherence to treatment, infection and exposure to allergens. When many people arrive at the same time with the same picture, the question changes: what happened in the environment they all shared?
What the scene teaches
In the opening scene, the patient has no asthma diagnosis, but she has seasonal rhinitis and was outdoors during the storm. Each of these clues, alone, seems minor. Together, they form the pattern. The post on signs, symptoms and history shows how context changes the weight of each finding. The WHO keeps a page on asthma with general information about the disease.
An outbreak, not a patient
Thunderstorm asthma is one of those pictures in which individual and public health reasoning meet. The first patient of the night may look like an ordinary attack. The tenth is already a sign that something larger is happening, and whoever notices the pattern early helps the service prepare for the next ones.
What happens in the air during the storm
Harun and colleagues explain that thunderstorm asthma arises when specific meteorological and aerobiological factors combine and reach predisposed people (Harun and colleagues, 2019). The storm's wind currents concentrate allergens at ground level, especially grass pollen. Humidity and rain rupture pollen grains through osmotic shock and release allergenic particles small enough to reach the lower airways.
From the nose to the bronchi
A whole pollen grain is large and generally stays trapped in the nose, which explains the rhinitis. The particles released when it ruptures are much smaller and can reach the bronchi. Harun and colleagues describe that inhaling these particles at high concentration by sensitized people can trigger an early asthmatic response, followed by a late inflammatory phase (Harun and colleagues, 2019). The authors also cite rapid temperature change and agricultural practices among the contributing factors.
The gust front
In the largest outbreak ever described, Thien and colleagues report that the grass pollen concentration was extremely high and that a gust front crossed the city in the early evening, dropping the temperature by 10 °C, raising humidity and concentrating particles in the air (Thien and colleagues, 2018). The storm does not need to be heavy in rain. What matters is the combination of wind, humidity and pollen at the right moment.
Why the weather clue disappears from the consultation
When the patient arrives at the emergency department, the storm has already passed. She talks about shortness of breath, wheezing and chest tightness, and rarely mentions the wind or the rain, because she sees no connection between the two. If nobody asks, the weather clue stays out. A simple question, such as "what were you doing when the symptoms started?", is usually enough to bring it back. In pollen season, also asking about the weather forecast and about other patients with the same picture on the same night helps separate an ordinary attack from an outbreak linked to the environment.
Outbreaks described in several places
Thunderstorm asthma is not a phenomenon of a single place. Packe and Ayres described an outbreak of acute asthma in a region of England in July 1983, with symptoms that began, in most patients, at the time of the sudden weather changes associated with a storm (Packe and Ayres, 1985). The authors found no role for air pollution and suggested that a sudden increase in fungal spores in the air may have contributed.
An outbreak within an hour
Venables and colleagues studied an asthma epidemic after a storm in southern and central England in June 1994 (Venables and colleagues, 1997). The storm was a mesoscale convective system, with several centers and strong wind gusts, and it occurred shortly after the grass pollen peak. The epidemic began within about an hour, possibly affected several thousand patients, overwhelmed emergency services and was short-lived. The patients had high serum levels of IgE against grass pollen.
The largest outbreak described
Thien and colleagues investigated the November 2016 outbreak in Melbourne, Australia, described as the largest and most catastrophic ever recorded (Thien and colleagues, 2018). In 30 hours, there were thousands more respiratory visits than expected in emergency services. Ten people died, and 35 were admitted to intensive care, all with asthma. Among the patients who answered the study questionnaire, only 28 in 100 had a current medical diagnosis of asthma.
The impact on emergency services
Andrew and colleagues analyzed the demand on the pre-hospital care service on the same day in Melbourne (Andrew and colleagues, 2017). Between six in the evening and midnight, the number of calls was 2.5 times higher than expected. After adjustment for trends in the period, the storm was associated with a 42 in 100 increase in total service demand, and calls for acute breathing difficulty were about five times more numerous than average.
Time is short
What distinguishes these outbreaks is speed. Venables and colleagues describe an epidemic that began within about an hour (Venables and colleagues, 1997), and Andrew and colleagues show the concentration of calls in the hours following the storm (Andrew and colleagues, 2017). For a service, this means little time to mobilize teams, medication and beds. For the clinician at the door, it means recognizing the pattern early.
Triage when everyone arrives at once
During an outbreak, the clinical question stops being only "what does this patient have?" and starts to include "who needs care first?". Patients with known and poorly controlled asthma, who speak with difficulty or who do not improve with the initial bronchodilator need immediate attention. The post on clinical decision-making shows how to weigh risks when time and resources are limited.
Who is most at risk
Lee and colleagues reviewed adult patients with thunderstorm asthma seen at a hospital during the 2016 outbreak (Lee and colleagues, 2017). About 60 in 100 had never received a diagnosis of asthma. On the other hand, allergic rhinitis during the grass pollen season was present in 99 in 100, sensitization to ryegrass pollen in all of them, and outdoor exposure during the storm in 94 in 100. The authors call this combination a trio of risk factors.

Seasonal rhinitis as a clue
The most important clue for the clinician may be rhinitis. Douglass and colleagues note that seasonal allergic rhinitis is present in the great majority of people who develop thunderstorm asthma (Douglass and colleagues, 2022). A person who sneezes every year in the same season and never had asthma can, on a stormy night, have the first attack of their life.
Known and poorly controlled asthma
Thien and colleagues found that a current medical diagnosis of asthma was linked to life-threatening attacks, such as those that required admission to intensive care (Thien and colleagues, 2018). Harun and colleagues also cite low adherence to preventive inhaled corticosteroid and previous admissions for asthma among the associated factors (Harun and colleagues, 2019). In other words, people without asthma can have the first attack, but people with poorly controlled asthma tend to have the worst ones.
Markers that help estimate risk
Douglass and colleagues studied adults with seasonal allergic rhinitis, with and without a history of thunderstorm asthma (Douglass and colleagues, 2022). All those who had been to hospital for thunderstorm asthma had a previous diagnosis of asthma. Lower forced expiratory volume in the first second and worse asthma control were associated with going to hospital. Higher specific IgE for ryegrass pollen, blood eosinophils and exhaled nitric oxide were associated with both symptoms and going to hospital.
Numbers that help separate groups
In the same study, a specific IgE for ryegrass pollen above 10.1 kU/L and a forced expiratory volume in the first second, before the bronchodilator, of up to 90 in 100 of predicted were markers of higher risk of going to hospital (Douglass and colleagues, 2022). The authors conclude that clinical tests can identify risk in people with seasonal rhinitis and guide treatment recommendations for each patient.
What to do with this information
These markers are not meant to diagnose the attack in the emergency department. They are meant for the visit before the pollen season, when the doctor can identify who is at higher risk and talk about prevention. The post on baseline rate in diagnosis explains how the probability of an event depends on the reference group. A person with seasonal rhinitis, sensitization to ryegrass and poorly controlled asthma belongs to a group with a risk very different from that of the general population.
Tests that fit into a routine visit
Some of the markers studied by Douglass and colleagues are part of common tests, such as spirometry and a blood count with eosinophil count (Douglass and colleagues, 2022). Others, such as specific IgE for a pollen and exhaled nitric oxide, depend on local availability. The reasoning does not require all of them. For most patients, the history of seasonal rhinitis, the question about asthma control and a spirometry already show who deserves more attention before the pollen season. Additional tests help refine the risk when doubt persists.
After the outbreak: the asthma that stays
Huang and colleagues followed people affected by the 2016 outbreak for five years (Huang and colleagues, 2022). The proportion with persistent asthma symptoms fell from 37 in 100 to 7 in 100 over the period, but only a minority reported being completely free of symptoms in each year. Prescription of inhaled preventer reached 67 in 100, and only 35 in 100 of patients used the medication regularly.


The first attack as a starting point
For the person who never had asthma, the thunderstorm attack can be the beginning of a disease that needs follow-up. Emergency care resolves the attack. The next appointment decides whether it happens again: confirm the diagnosis, assess lung function, treat rhinitis and agree on an action plan.
Immunotherapy is still an open question
In the same study, Huang and colleagues tested in an open-label way a sublingual immunotherapy with grass pollen and found no difference in rhinitis symptoms or asthma control compared with the control group (Huang and colleagues, 2022). The authors note that there was no new thunderstorm during the study to test a protective effect. The question remains open, and it is a good example of how the evidence can be limited precisely by the rare nature of the event.
Prevention, alert and action plan
Price and colleagues describe thunderstorm asthma as a global health problem that can arrive without sufficient warning and note that, with climate change, future events may become more common and more unpredictable (Price and colleagues, 2021). The authors argue that identifying people at risk and their markers is the most preventive way to reduce the consequences of these outbreaks.
What changes in the appointment
The table below summarizes, in a teaching way, risk profiles and useful questions before the pollen season. It simplifies a complex topic and does not replace local guidelines.
| Profile | Why it matters | Question that helps |
|---|---|---|
| Seasonal allergic rhinitis, without asthma | Many affected people never had asthma | Do you have sneezing and a runny nose in the same season every year? |
| Sensitization to grass pollen | It is part of the risk trio | Have you had an allergy test, and what are you sensitive to? |
| Known and poorly controlled asthma | Linked to the most severe attacks | How often do you use the reliever bronchodilator? |
| Poor adherence to the preventer | Associated with the risk of an attack | Do you use the preventer every day, even without symptoms? |
| Outdoor exposure during thunderstorms | The risk trio includes exposure | Does your work or routine force you to stay outside in the late afternoon? |
Staying inside, with windows closed
Harun and colleagues describe, among the measures discussed for people at risk, avoiding staying outdoors during thunderstorms in the pollen season and keeping preventive treatment up to date (Harun and colleagues, 2019). Guidance like this depends on each place's alert systems and local guidelines, but the conversation can start in any routine appointment with someone who has seasonal rhinitis.
The biases that leave the weather out
Thunderstorm asthma rarely goes unnoticed for lack of knowledge. It usually slips through predictable habits and biases:
- Thinking that asthma only happens in those who already have the diagnosis.
- Treating the attack and not asking about seasonal rhinitis and pollen sensitization.
- Not asking where the patient was and what happened with the weather in the previous hours.
- Seeing each patient as an isolated case during an outbreak.
- Ending the appointment without a follow-up plan after a first attack.
Croskerry describes anchoring and premature closure among the most frequent cognitive errors in diagnosis (Croskerry, 2003). The post about diagnostic pause shows how a short moment of checking helps to notice what was left out.
Back to the scene
In the opening scene, the patient receives treatment for the attack and improves. The reasoning, however, does not end there. The doctor asks about the rhinitis, about when the shortness of breath began and about what she was doing at the time of the storm. She notices that other patients arrived with the same picture on the same night and alerts the team. At discharge, she arranges a follow-up visit to confirm the diagnosis of asthma, assess sensitization and talk about prevention in the next pollen season.
How NEXO helps train this reasoning
In NEXO, the case of the day is fictional, with a real clinical presentation and up to six progressive clues. You propose a diagnosis by searching for the code in ICD-10 and receive proximity feedback at five levels, which shows whether the guess landed on the exact code, the same category, the same group, the same chapter or a different chapter. This format speaks to the theme of this text: a clue about the weather or the season can move a guess from a respiratory infection to an allergic disease of the airways.
To use the case of the day as training, try three habits. Before each guess, ask what happened in the patient's environment in the previous hours. When a clue about allergy appears, ask how it changes the list. After the result, note which clue would have anticipated the diagnosis.
Three exercises with cases
Ask about the previous day. In each respiratory case, imagine the weather and the season and see if anything changes.
Look for the trio. Faced with an attack of shortness of breath, check for seasonal rhinitis, sensitization and exposure.
Think about the outbreak. Reread a case imagining that ten patients arrived with the same picture on the same night.
The post about case-based learning with clinical cases shows how cases help fix patterns that rarely appear in daily practice.
The limits on using the game are described on the NEXO Economy page. If you research the teaching of clinical reasoning, the page for Researchers explains how to get in touch. Professionals who write or review cases find information under Curator and Creators, and institutions can learn about the proposal on the partnerships page.
Frequently asked questions
What is thunderstorm asthma?
It is the onset of acute asthma attacks soon after a thunderstorm, during the pollen season. It can affect many people at the same time.
Why does a thunderstorm trigger attacks?
The wind concentrates pollen at ground level, and humidity ruptures the grains, releasing small particles that reach the bronchi of sensitized people.
Can someone who has never had asthma have an attack during a thunderstorm?
Yes. In one of the studies of the largest outbreak described, most of the adults treated had never received a diagnosis of asthma, but almost all had seasonal allergic rhinitis.
Who is at higher risk of a severe attack?
People with known, poorly controlled asthma, low adherence to the preventer and previous hospitalizations for asthma tend to have the most severe attacks.
What should be done after a first attack?
Seek a follow-up visit to confirm the diagnosis, assess lung function, treat the rhinitis and agree on an action plan for the next season.
How can you prepare for the pollen season?
Keep the preventer up to date when indicated, have an action plan, follow local alerts and avoid staying outdoors during thunderstorms at this time of year.
Final checklist
- I asked about seasonal allergic rhinitis and pollen sensitization.
- I asked where the patient was and what happened with the weather in the previous hours.
- I considered asthma even without a previous diagnosis.
- I noticed when several patients arrived with the same picture and alerted the team.
- I assessed asthma control and adherence to the preventer in those who already had the diagnosis.
- I arranged follow-up and an action plan before the next pollen season.
Want to practice reasoning with progressive clues? Play the case of the day.
References
- Andrew E, Nehme Z, Bernard S, et al. Stormy weather: a retrospective analysis of demand for emergency medical services during epidemic thunderstorm asthma. BMJ. 2017. PMID 29237604.
- Croskerry P. The importance of cognitive errors in diagnosis and strategies to minimize them. Acad Med. 2003. PMID 12915363.
- Douglass JA, Lodge C, Chan S, et al. Thunderstorm asthma in seasonal allergic rhinitis: the TAISAR study. J Allergy Clin Immunol. 2022. PMID 34774618.
- Harun NS, Lachapelle P, Douglass J. Thunderstorm-triggered asthma: what we know so far. J Asthma Allergy. 2019. PMID 31190900.
- Huang F, Wang DH, Foo CT, et al. The Melbourne epidemic thunderstorm asthma event 2016: a 5-year longitudinal study. Asia Pac Allergy. 2022. PMID 36452015.
- Lee J, Kronborg C, O'Hehir RE, Hew M. Who's at risk of thunderstorm asthma? The ryegrass pollen trifecta and lessons learnt from the Melbourne thunderstorm epidemic. Respir Med. 2017. PMID 29229087.
- Packe GE, Ayres JG. Asthma outbreak during a thunderstorm. Lancet. 1985. PMID 2862383.
- Price D, Hughes KM, Thien F, Suphioglu C. Epidemic thunderstorm asthma: lessons learned from the storm down-under. J Allergy Clin Immunol Pract. 2021. PMID 33172604.
- Thien F, Beggs PJ, Csutoros D, et al. The Melbourne epidemic thunderstorm asthma event 2016: an investigation of environmental triggers, effect on health services, and patient risk factors. Lancet Planet Health. 2018. PMID 29880157.
- Venables KM, Allitt U, Collier CG, et al. Thunderstorm-related asthma: the epidemic of 24/25 June 1994. Clin Exp Allergy. 1997. PMID 9249264.
- World Health Organization. Asthma. Information page.