Diphtheria returns: pseudomembrane, antitoxin, macrolide
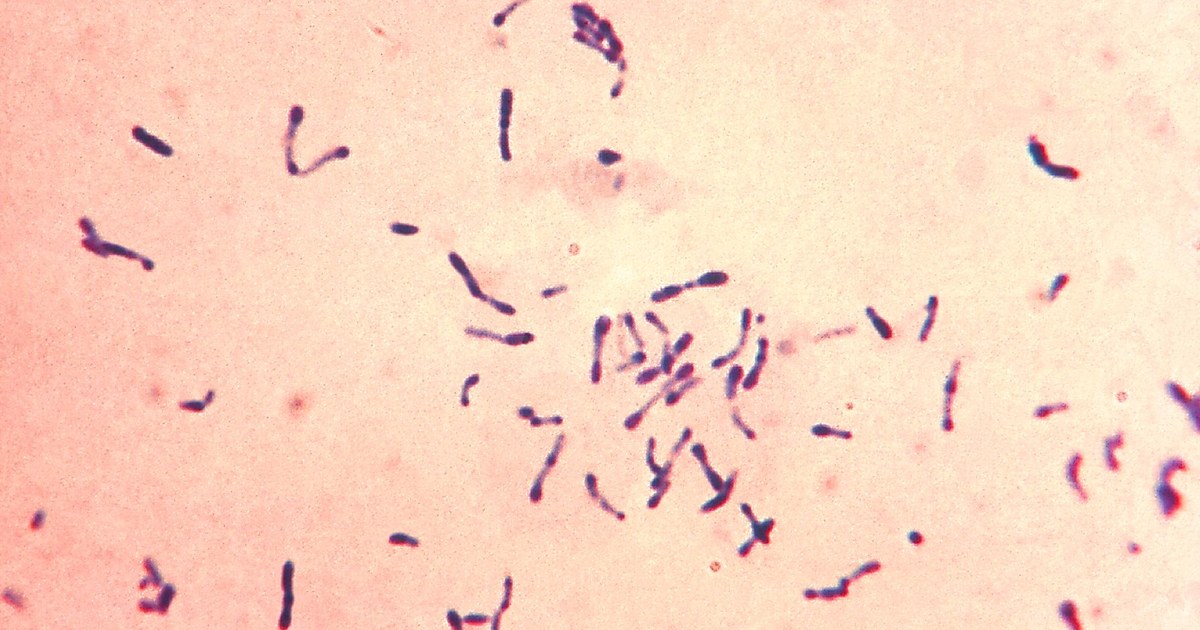
Table of contents
- Why diphtheria is a reasoning scenario
- The clinical picture: pseudomembrane and bull neck
- The differential diagnosis of sore throat with plaque
- Laboratory confirmation: important, but not for deciding whether to start
- Antitoxin: early and without routine sensitivity testing
- Antibiotic: macrolide preferred over penicillin
- Airway, heart and nerves: the complications
- Contacts, isolation and vaccination
- When vaccination falls: outbreaks in various settings
- Early closure in the face of tonsillitis
- How NEXO helps train this reasoning
- Frequently asked questions
- Final checklist
- References
In an emergency department, a seven-year-old girl arrives with a sore throat, low fever and a nasal voice for two days. Her mother says the girl is quieter than usual, barely eats and breathes through her mouth. On examination there is a grayish plaque over the tonsils that extends to the uvula, and the neck looks swollen. The vaccination card was left incomplete after a move to another city. The first hypothesis of the clinician on duty may be ordinary bacterial tonsillitis. The scene is fictional and was written for teaching. This text uses that picture as a clinical reasoning scenario: how to recognize diphtheria when it reappears, why antitoxin must be given early and without waiting for confirmation, why the macrolide is preferred to penicillin in the most recent guideline and what to do with contacts.
NEXO is a daily medical diagnosis game: one clinical case a day, up to six progressive clues, and ICD-10 proximity feedback across five levels.
The text is not a treatment protocol. Antitoxin and antibiotic doses, notification and access pathways to antitoxin follow national guidelines and the training of each service. The interest here is reasoning: why a disease many professionals have never seen demands quick decisions, made before the laboratory result. If you play the case of the day in NEXO, you will recognize the move: a visual clue can shift the hypothesis from a common condition to an emergency.
Key points
- Respiratory diphtheria presents with a grayish, adherent pseudomembrane that bleeds when removal is attempted.
- Bull neck, from edema and lymph nodes, is a sign of severe disease.
- Antitoxin should be given as soon as possible, based on clinical suspicion, without waiting for laboratory confirmation.
- The 2024 World Health Organization guideline does not recommend routine sensitivity testing before antitoxin, but calls for preparation for anaphylaxis.
- The same guideline prefers macrolides to penicillin, and contacts receive prophylaxis and vaccination updates.
Why diphtheria is a reasoning scenario
Diphtheria is an infection caused by toxigenic strains of Corynebacterium diphtheriae and, more rarely, of related species. Diphtheria toxin accounts for most of the severity: it damages tissue at the site of infection and, at a distance, can reach the heart and the nerves. Sharma and colleagues reviewed the disease and recalled that, despite an effective vaccine available for decades, diphtheria continues to cause outbreaks where vaccination coverage falls (Sharma and colleagues, 2019).
That is the central point of the scenario. In places with good vaccination, diphtheria has become rare, and many professionals have never seen a case. When vaccination coverage falls because of humanitarian crises, population displacement, conflicts or distrust of vaccines, the disease returns. And it returns for teams that need to recognize it without prior experience.
What the scene teaches
The scene has four clues. The first is the grayish plaque that extends beyond the tonsils, which is unusual for ordinary bacterial tonsillitis. The second is the swollen neck. The third is the nasal voice, which may indicate involvement of the palate. The fourth is incomplete vaccination. Separately, each has other explanations. Together, they make diphtheria a hypothesis that must be considered before any result.
The post on differential diagnosis shows how a clue that does not fit the main hypothesis should make room for another.
The clinical picture: pseudomembrane and bull neck
The diphtheria chapter of the Centers for Disease Control and Prevention Pink Book describes the classic respiratory form (Centers for Disease Control and Prevention, 2024). Onset is usually gradual, with sore throat, low fever and malaise. Within a few days a grayish, adherent membrane forms over the tonsils, pharynx, palate or larynx. When removal is attempted, it bleeds.
In severe forms, soft tissue edema and enlarged lymph nodes give the neck the appearance described as bull neck. The membrane can extend to the larynx and trachea and obstruct the airway. The 2024 World Health Organization guideline on clinical management of diphtheria defines as severe disease cases with symptoms for three days or more, bull neck, respiratory distress or shock (World Health Organization, 2024).
Other forms
Diphtheria can also affect the nose, with serosanguineous discharge on one side only, and the skin, with chronic ulcers that can serve as a reservoir for transmission. The cutaneous form is more common in hot climates and in people with poor housing conditions. It can be mild, but it is contagious and can coexist with other skin infections.
Children, adolescents and adults
Diphtheria is classically described in children, but recent outbreaks have also affected adolescents and adults, especially when childhood vaccination was incomplete or when immunity waned without booster doses. In adults, sore throat can be attributed to viral pharyngitis, and the membrane may be less extensive. In young children, airway obstruction happens faster because the airway is narrow. The question about vaccination should be asked at any age, including booster doses in adolescence and adult life.
Incubation and transmission
Transmission happens through respiratory droplets and contact with skin lesions. The World Health Organization guideline describes an incubation period of two to five days (World Health Organization, 2024). The pooled analysis by Truelove and colleagues found a short median incubation period and showed that vaccinated people can carry and transmit the bacterium, even when they have milder disease (Truelove and colleagues, 2020).
Nasal and cutaneous diphtheria in practice
The nasal form is usually mild, but it misleads: a bloody discharge on one side only, in a child, can be attributed to a foreign body or a cold. The cutaneous form appears as a shallow ulcer, sometimes with a grayish membrane at the base, over insect bites, wounds or other skin lesions. In both situations, the question is the same: was there contact with cases, is vaccination incomplete, is there an outbreak in the region? When the answer is yes, collecting material from the lesion for culture and isolating the person prevents a mild case from becoming a source of transmission to more vulnerable people.
The differential diagnosis of sore throat with plaque
Plaques on the tonsils are common, and most are not diphtheria. The challenge is to notice when the presentation departs from what is expected. The table below summarizes useful clues.
| Condition | Clues in favor | Clues that resemble diphtheria |
|---|---|---|
| Diphtheria | Grayish, adherent membrane that bleeds when removed and extends to the uvula or palate; bull neck; incomplete vaccination | Low fever, sore throat |
| Streptococcal tonsillitis | White-yellowish exudate that detaches easily, high fever, abrupt onset | Tonsillar plaque, cervical lymph nodes |
| Infectious mononucleosis | Extensive exudate, posterior cervical lymph nodes, enlarged spleen, intense fatigue | Extensive plaque and enlarged neck |
| Vincent angina | Ulcer with necrosis, marked bad breath, poor oral hygiene | Grayish membrane |
| Oral candidiasis | White plaques that can be removed, immunosuppression or antibiotic use | Plaques in the oropharynx |
| Peritonsillar abscess | Asymmetry, deviation of the uvula, trismus, muffled voice | Intense pain and cervical edema |
What most distinguishes diphtheria is the adherence of the membrane and its extension beyond the tonsils. The Pink Book notes that the membrane bleeds when one tries to remove it (Centers for Disease Control and Prevention, 2024). Trying to pull it off to test is not recommended; observation is already enough for suspicion.
Vaccination history as a clue
Asking about vaccination is part of the diagnosis. An incomplete record does not confirm diphtheria, and a complete record does not rule it out, but the information changes the probability. The post about pretest probability shows how contextual information changes the weight of each clinical finding.
Laboratory confirmation: important, but not for deciding whether to start
The diagnosis of diphtheria is clinical. Confirmation comes from culture of throat or membrane material, followed by demonstration that the strain produces toxin, by the Elek test or by PCR for the toxin gene (Centers for Disease Control and Prevention, 2024). These tests can take days and are not always available near where the patient is.
That is why the Pink Book and the World Health Organization guideline agree on one point: antitoxin and antibiotic should start based on clinical suspicion, without waiting for confirmation (World Health Organization, 2024). The sample should be collected before the antibiotic, if possible, but collection should not delay treatment.


Why waiting costs dearly
Antitoxin neutralizes only the toxin that is still circulating, not the toxin that has already bound to tissues (World Health Organization, 2024). Every hour of waiting allows more toxin to bind to the heart, the nerves and the tissues of the throat. Waiting for the culture to start antitoxin is, in practice, accepting greater harm. The post about diagnostic uncertainty discusses how to act safely when the cost of waiting is greater than the cost of treating.
Antitoxin: early and without routine sensitivity testing
Diphtheria antitoxin is produced from horse serum. For that reason, a sensitivity test before administration was recommended for a long time, to predict allergic reactions. The 2024 World Health Organization guideline changed this guidance: it does not recommend routine sensitivity testing before antitoxin, because it does not predict reactions well and delays treatment, and it asks that the team be prepared to treat anaphylaxis (World Health Organization, 2024).
Field experience supports this approach. Eisenberg and colleagues described the use of antitoxin during a large outbreak among Rohingya refugees and showed that administration was safe with monitoring in a basic critical care setting, with generally mild reactions (Eisenberg and colleagues, 2021).
Dose and shortage
The amount of antitoxin depends on the severity and duration of the illness, according to regimens defined in the guideline and in national protocols, which are not reproduced here. A practical problem is the global shortage of antitoxin, noted by the World Health Organization guideline (World Health Organization, 2024). Knowing how to obtain it quickly within one's own service or through the referral network is part of the preparation.
Preparing the service before the first case
In a service where diphtheria is rare, the first case usually reveals gaps: nobody knows where to request antitoxin, the laboratory lacks a suitable culture medium and the team does not remember the isolation criteria. Training these steps in advance, with a written flow and updated contacts for the referral network, reduces the time between suspicion and treatment. The World Health Organization guideline treats access to antitoxin as part of clinical management, not as a separate logistics problem (World Health Organization, 2024).
A common reasoning error
Faced with a rare disease and a treatment with a risk of reaction, the temptation is to wait for more certainty. The reasoning seems prudent, but it reverses the priorities. In severe diphtheria, the risk of not giving antitoxin in time is usually greater than the risk of a treatable reaction. The post about clinical decision-making discusses how to compare the risks of acting and of not acting.
Antibiotic: macrolide preferred over penicillin
The antibiotic eliminates the bacterium, interrupts toxin production and reduces transmission. It does not replace antitoxin. Truelove and colleagues recalled that antibiotics must be combined with antitoxin in clinical cases (Truelove and colleagues, 2020).
The 2024 World Health Organization guideline brings a strong recommendation: use macrolides, such as azithromycin or erythromycin, in preference to penicillin to treat diphtheria (World Health Organization, 2024). The choice of drug, route and duration follow the guideline and local protocols, according to severity and ability to swallow.
When the patient stops transmitting
The Pink Book reports that a person usually stops being contagious about two days after starting the appropriate antibiotic, but ending isolation often depends on two negative cultures collected after treatment (Centers for Disease Control and Prevention, 2024). Criteria vary between countries and follow local guidelines.
Airway, heart and nerves: the complications
The most immediate threat of respiratory diphtheria is airway obstruction by the membrane and by edema. The World Health Organization guideline notes that airway interventions may be necessary and that they should be done by experienced professionals, because manipulating the throat can dislodge the membrane (World Health Organization, 2024). Signs such as stridor, retractions, agitation and falling oxygen saturation call for urgent assessment.
Myocarditis is the most feared severe complication at a distance. The Pink Book describes that it can appear early or weeks after onset, with arrhythmias and heart failure (Centers for Disease Control and Prevention, 2024). Neurological complications follow their own timeline: palatal paralysis in the third week, with a nasal voice and nasal regurgitation, and other paralyses, including of peripheral nerves, after the fifth week.


Follow-up after the acute phase
Because cardiac and neurological complications can appear late, discharge does not end care. Ahmed and colleagues studied children with diphtheria in a hospital with few resources and found myocarditis and neuritis among the factors associated with severity (Ahmed and colleagues, 2026). Monitoring the heart in the acute phase and advising the family about signs of worsening in the following weeks is part of treatment.
Contacts, isolation and vaccination
A person with diphtheria should be isolated with droplet precautions, and with contact precautions when there are skin lesions. Close contacts, such as people living in the same house and people exposed to secretions, should be identified, examined and followed up. The Pink Book recommends that they receive antibiotic prophylaxis and updated vaccination (Centers for Disease Control and Prevention, 2024).
Polonsky and colleagues described the response to a large outbreak among refugees and showed the importance of contact tracing, prophylaxis and maintaining access to routine vaccination during humanitarian crises (Polonsky and colleagues, 2021).
Exposed health professionals
Professionals who examined the throat, suctioned secretions or managed the airway without adequate protection are also contacts. They should be assessed, receive prophylaxis according to protocol and have their vaccination checked. Wearing a mask and eye protection from the moment of suspicion, not only after confirmation, reduces these exposures. In an outbreak, protecting the team is also a way to protect the service's capacity to keep providing care.
The disease does not protect
A surprising detail: having diphtheria does not guarantee immunity. For this reason, the Pink Book recommends vaccinating the person during convalescence, completing the schedule according to age (Centers for Disease Control and Prevention, 2024). Truelove and colleagues found high effectiveness with the complete primary schedule, which reinforces that vaccination is the main form of prevention (Truelove and colleagues, 2020).
When vaccination falls: outbreaks in various settings
Diphtheria has reappeared in very different places over the last decades. Zakikhany and Efstratiou reviewed the return of cases in Europe and highlighted the importance of maintaining laboratory surveillance and diagnostic capacity even where the disease has become rare (Zakikhany and Efstratiou, 2012). Al-Dar and colleagues described the resurgence in a context of prolonged conflict, with interrupted access to routine vaccination (Al-Dar and colleagues, 2022).
These contexts have something in common. The drop in vaccination coverage rarely happens for a single reason. It can come from conflicts, population displacement, collapse of health services, access difficulties or vaccine hesitancy. In all cases, the clinical result looks the same: unvaccinated children and adults with sore throat and a plaque that no one on the team had seen before.
Mortality and the time to treatment
The World Health Organization guideline recalls that the lethality of untreated diphtheria in unvaccinated people reaches almost one third of cases, and that in some outbreaks it approached half (World Health Organization, 2024). These numbers do not describe a disease without possible treatment. They describe the cost of delay, of the lack of antitoxin and of the lack of vaccination. The earlier the suspicion is raised and the antitoxin reaches the patient, the smaller the damage caused by the toxin to the heart, nerves and airway tends to be.
Early closure in the face of tonsillitis
Croskerry described early closure as the tendency to accept a hypothesis before it is verified (Croskerry, 2003). Faced with a child with sore throat and plaque, "it's tonsillitis" is the most likely hypothesis in most places. The problem arises when the high probability makes the team ignore the clue that does not fit: the adherent membrane, the extension to the palate, the swollen neck, the incomplete vaccination.
The post about diagnostic pause describes a simple question that helps in these situations: what does not fit with the main hypothesis? The post about examples of heuristics in clinical reasoning shows how shortcuts that work almost always can fail precisely in rare and severe cases. And the post about clinical reasoning exercises for pediatrics brings ways to train this eye in cases of children.
How NEXO helps train this reasoning
In NEXO, the case of the day is fictional, with a real clinical presentation and up to six progressive clues. You propose a diagnosis by searching for the ICD-10 code and receive proximity feedback in five levels, which shows whether the guess stayed at the exact code, in the same category, in the same group, in the same chapter or in another chapter. This format speaks to the theme of this text: tonsillitis and diphtheria can start out similar, but the right clue changes the code and the urgency.
To use the case of the day as training, try three habits. Before each guess, ask which clue does not fit with the most common hypothesis. When the case involves a vaccine-preventable disease, ask about the vaccination history. After the result, note which clue would have anticipated the diagnosis.
Three exercises with cases
Look for what does not fit. Faced with a common presentation, identify the finding that stands out and ask what it suggests.
Decide before the exam. In severe cases, list the decisions that need to be made before the result arrives.
Think about the context. Ask how the diagnosis would change if the person came from a place with low vaccination coverage.
The post about case-based learning shows how cases help recognize diseases that rarely appear in daily practice.
The limits of use of the game are described on the NEXO economy page. If you research teaching of clinical reasoning, the page for researchers explains how to get in touch. Professionals who write or review cases find information in curation and in creators, and institutions can learn about the proposal on the partnerships page.
Frequently asked questions
Is the diagnosis of diphtheria clinical?
Yes. Clinical suspicion is enough to start antitoxin and antibiotic, and confirmation by culture and toxin test comes later.
Should antitoxin be given without waiting for confirmation?
Yes. It only neutralizes the toxin that has not yet bound to tissues, so it should be given as soon as possible.
Does the current guideline waive routine sensitivity testing before antitoxin?
Yes. The 2024 World Health Organization guideline does not recommend routine testing and calls for preparation to treat anaphylaxis.
Is a macrolide preferred over penicillin?
Yes. The same guideline gives a strong recommendation for macrolides over penicillin.
Do people who had diphtheria need to be vaccinated?
Yes. The disease does not guarantee immunity, so vaccination should be done during convalescence.
Can vaccinated people transmit the bacteria?
Yes. Vaccinated people can carry and transmit the bacterium, usually with milder disease, so contacts are assessed regardless of vaccination.
Final checklist
- I checked whether the membrane is grayish, adherent and extends beyond the tonsils.
- I assessed the neck, the airway and signs of severity.
- I asked about vaccination and possible contacts.
- I collected material for culture and toxin testing without delaying treatment.
- I requested antitoxin based on the clinical suspicion.
- I prepared the team to treat anaphylaxis.
- I started an antibiotic, with a preference for a macrolide.
- I isolated the patient and identified the contacts.
- I planned cardiac monitoring and neurological follow-up.
- I scheduled vaccination for convalescence.
Want to practice your reasoning with progressive clues? Play the case of the day.
References
- Ahmed FA, Ali MN, Hassan MY, et al. Clinical recognition of pediatric diphtheria in a resource-limited Somali hospital: a prospective observational study. Trop Med Health. 2026. PMID 42402610.
- Al-Dar AA, Al-Qassimi M, Ezzadeen FH, et al. Diphtheria resurgence in Sada'a-Yemen, 2017-2020. BMC Infect Dis. 2022. PMID 35016630.
- Centers for Disease Control and Prevention. Epidemiology and Prevention of Vaccine-Preventable Diseases (Pink Book). Chapter 7: Diphtheria. 2024. Document.
- Croskerry P. The importance of cognitive errors in diagnosis and strategies to minimize them. Acad Med. 2003. PMID 12915363.
- Eisenberg N, Panunzi I, Wolz A, et al. Diphtheria antitoxin administration, outcomes, and safety: response to a diphtheria outbreak in Cox's Bazar, Bangladesh. Clin Infect Dis. 2021. PMID 33245364.
- World Health Organization. Clinical management of diphtheria: guideline. 2024. Document.
- Polonsky JA, Ivey M, Mazhar MKA, et al. Epidemiological, clinical, and public health response characteristics of a large outbreak of diphtheria among the Rohingya population in Cox's Bazar, Bangladesh, 2017 to 2019: a retrospective study. PLoS Med. 2021. PMID 33793554.
- Sharma NC, Efstratiou A, Mokrousov I, et al. Diphtheria. Nat Rev Dis Primers. 2019. PMID 31804499.
- Truelove SA, Keegan LT, Moss WJ, et al. Clinical and epidemiological aspects of diphtheria: a systematic review and pooled analysis. Clin Infect Dis. 2020. PMID 31425581.
- Zakikhany K, Efstratiou A. Diphtheria in Europe: current problems and new challenges. Future Microbiol. 2012. PMID 22568715.